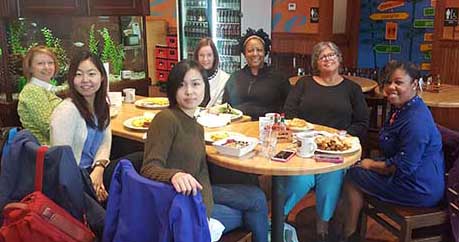Skip to content

Posts from the ‘Editor’s Picks’ Category

Nursing Influence


The latest featured article in the current issue of ANS is titled “Understanding Influence within the Context of Nursing: Development of the Adams Influence Model Using Practice, Research, and Theory” authored by Jeffrey M. Adams, PhD, RN, NEA-BC, FAAN and Sudha Natarajan, PhD, MSN, RN.  While it is featured it is available for download at no cost, so I invite you to read the article and return here to share in discussion of these important ideas!  Here is a message from Dr. Adams about this work:

The Adams Influence Model (AIM) can be used as a framework for anyone seeking to understand more about the factors, attributes, and process of influence.  However, the concept of influence is an especially important one for

Jeffrey Adams

Jeffrey Adams

nurses.  The basis of exploration of influence highlighted in this article started well over ten years ago and drew from years of experiences as a consultant working in the clinical information systems (CIS) space.  At that time, I found that CISs were largely selected by CFOs, CIOs, CMOs and I felt that while nurses were “involved” in the selection process, often times product chosen did not benefit nursing care or capture nursing data.  This was despite nurses overwhelmingly being the largest users of the CIS.  I wanted to simply understand why or how this happened?

Around that same time RWJF and Gallup released a report identifying that respondents did not perceive nursing as influential in reshaping health policy (what is now the ACA) when compared to nearly every other group.  And several other smaller studies also identified that executive nurses self reported as having less influence than their non-nurse executive counterparts on a host of issues.  So we thought, how could this be?  At 1% of the entire US population nurses are by far the largest percentage of the healthcare workforce, nurses are overwhelmingly the most trusted profession, and nurses are well documented addressing each component of the quadruple aim.  Of course nurses SHOULD be influential… and because we aren’t, how do we get there?  We decided to start at the beginning and asked the question “what does influence look like?” The AIM, as represented in this article, is the result of our efforts to answer that question.

While the origins and development of the AIM are chronicled in this manuscript, the AIM has been widely used since 2009 to frame health policy and strategy, to describe leadership practices, and serve as a guiding framework for research and instrument development.

Current projects using the AIM include development of:

  • understanding nursing leadership’s influence over professional practice environments and the relationship to workforce and patient outcomes (with Maja Djukic, Ashley-Kay Basile and Matt Gregas)
  • a guiding framework for baccalaureate health policy curriculum (with Ashley Waddell and Jaqueline Fawcett).
  • the influence of nurse leaders on the professional practice environment and nurse engagement (with Maria Ducharme, Jeannie Bernstein, and Cynthia Padula)
  • Leadership Influence Self Assessment (LISA©) instrument (with RWJF Executive Nurse Fellows colleagues Debbie Chatman Bryant, Joy Deupree, Suzanne Miyamoto, Casey Shillam and Matt Gregas).

It would be wonderful to see everyone take inventory and articulate how we anticipate each of our projects, papers, presentations, courses and other efforts will INFLUENCE practice, research, education, theory and/or policy.  This “influence” framing provides us opportunity to be purposeful and forward thinking toward an end that doesn’t leave assimilation of our contributions and value to chance.


Learner-Centered Clinical Growth


In the current ANS featured article, author Jessica Barkimer, MSN, RN, CNE illustrates the value of evolutionary concept analysis to understand a dynamic, changing phenomena – clinical growth.  The article, titled “Clinical Growth: An Evolutionary Concept Analysis” is available at no charge while it is featured on the ANS website!  Here is Ms. Barkimer’s description of her work that led to this article:

As an educator who teaches nursing students in various clinical learning environments, I embrace the student-centered approach.  Each student brings forth unique previous experiences that contribute to his or her own construction of knowledge.  Years ago, while working on my degree, Masters of Science in Nursing Education, I encountered students who were functioning at various levels in the same cohort of students.  Learning objectives

Jessica Barkimer

Jessica Barkimer

often guide educators, however, in an attempt to facilitate the learning of each student, I often wondered, “how can an educator determine if a student demonstrates an appropriate amount of growth to progress to the next level?”  This multifaceted topic requires examination to benefit nurse educators, students, and patients.  Currently, I am working towards my PhD in nursing and have had the opportunity to work with faculty at Marquette University who have helped guide me in this process of knowledge discovery.

This article presents the findings of the conceptual analysis of clinical growth, using Rodger’s evolutionary method.  These findings represent a holistic approach, focusing on cognitive, affective, and psychomotor domains of each learner, requiring growth in all three areas.  This concept analysis and model lay the foundational groundwork for examining relationships among the antecedents, attributes, and consequences, which are essential for a nurse educator to understand and implement in practice, moving nursing education forward.  This examination of the literature also allowed me to consider various instruments designed to capture the aspects of clinical growth.  I look forward to continuing my research in this area.

Internet Recruitment of Racial/Ethnic Minority Research Participants


The currently featured article in ANS presents an examination of six practical issues the authors encountered in recruiting Asian-American breast cancer survivors as participants in an intervention study conducted on the internet.  The article is titled “Internet Recruitment of Asian American Breast Cancer Survivors,” authored by Eun-Ok Im, PhD, MPH, RN, CNS, FAAN; Yaelim Lee, PhD, RN; Xiaopeng Ji, MSN, RN; Jingwen Zhang, PhD; Sangmi Kim, MSN, RN; Eunice Chee, BSE; Wonshik Chee, PhD; Hsiu-Min Tsai, PhD, FAAN; Masakazu Nishigaki, PhD, RN, PHN, CGC; Seon Ae Yeo, PhD, FAAN; Marilyn M. Shapira, MD, MPH; Jun James Mao, MD, MSCE.  This informative article is availabe at no charge while it is featured; we invite you to read the article and contribute your responses to the article here!

Nurse Fatigue in the Hospital


The latest featured article from the current issue of ANS  is titled “Interpretation of Hospital Nurse Fatigue Using Latent Profile Analysis” by Diane Ash Drake, PhD, RN and Linsey M. Barker Steege, PhD. You can access this article here at no charge now while it is featured. Dr. Drake and Dr. Steege have each provided a message about their background and the work that has led to this article!  Leave your comments here to join a conversation about their work.

From Diane Drake –

diane-drake

Diane Ash Drake

I have had the privilege to consult as the Nurse Research Scientist at Mission Hospital, Mission Viejo, CA since 2003. Nurse fatigue quickly became a focused research interest supported by a small team of hospital nurse leaders who understood the potential adverse effects of long work shifts, and wanted to better understand hospital nurse fatigue and investigate fatigue risk management strategies. During the initial literature search we reviewed several nurse fatigue dissertations and contacted one investigator, a human factors engineer, who fortunately joined our study team. I want to thank Dr. Linsey Steege who shares the authorship of this paper with me for her perseverant collaboration and brilliant research intellect. Ultimately, my investigation of hospital nurse fatigue is about supporting the important work of hospital nurses with the purpose of making fatigue risk management a reality.

From Linsey Steege –

barker_linsey

Linsey M. Barker Steege

As an industrial and systems engineer, my overall research goal is to design work systems to improve health, safety and performance of health professionals, and by doing so, to benefit society by improving healthcare quality and patient outcomes. Human factors engineering is a focus area within industrial and systems engineering, which examines the interactions between humans, tools and technologies, the physical environment, and the organization of work in an effort to optimize human performance and well-being. In recent years, multiple agencies including the Institute of Medicine, the President’s Council of Advisors on Science and Technology, the National Academy of Engineering, and the Agency for Healthcare Research and Quality have pointed to the importance of partnership and collaboration between systems engineering, including human factors engineering, and healthcare. I feel privileged to be able to collaborate with Dr. Drake and the Mission Hospital nurse fatigue study team to better understand nurse fatigue in the context of the hospital nurse work system and work toward improved fatigue monitoring and risk management systems.  The findings from this paper offer a new approach for measuring nurse fatigue and may be useful in developing more efficient fatigue monitoring systems and for evaluating the effect of fatigue risk management strategies.


Trauma Informed Nursing Practice with Teen Mothers


The current ANS featured article is authored by Sarah Bekaert, MSc and Lee SmithBattle, PhD, and is titled “Teen Mothers’ Experience of Intimate Partner Violence: A Metasynthesis.”  We invite you to download this article from the ANS website and return here to add you comments to a discussion of this very important issue.  Sarah Bekaert shared this background about this article:

This paper arose from the two authors’ mutual interest in the lived experience of teen mothers.  Sarah Bekaert is currently lecturing at City University, London, UK, and practicing clinically in Sexual Health and Contraception with Oxford University Hospitals Trust.  A Children’s nurse by background, she has a special interest in teen health,

Sarah Bekaert

Sarah Bekaert

pregnancy and parenthood.  Her current PhD study explores the tension between public expectations for avoiding teen mothering and the private desire of some teens who have had a previous abortion to become a mother whilst still a teen.

Professor Lee SmithBattle of St Louis University, U.S., is a nurse who is currently on the seventh round of interviews with former teen mothers and their families.  Spanning 30 years, this qualitative longitudinal study challenges the pejorative assumptions of teen mothers by contextualizing their experiences and long-term outcomes.

With the explosion of qualitative research on teen mothering, Professor SmithBattle drew together a team to organize, summarize and review this research.  This first metasynthesis project focuses on intimate partner violence (IPV) in teen mother’s relationships.

Lee SmithBattle

Lee SmithBattle

We have organized our findings by the metaphor of a spider’s web to illustrate the trajectory of IPV in the young mother’s lives and attempts to extricate themselves from violent relationships.  The metaphor was inspired by a verse from the poem ‘Integrity’ by Adrienne Rich1, American poet, essayist and radical feminist of the 20th and early 21st century.*

Bekaert Fig1

Findings highlight pervasive violence in teen mothers’ childhoods and impoverished circumstances that make it difficult to leave an abusive relationship. We observe a constriction of the web as domestic violence emerges or worsens with pregnancy. As a consequence, young mothers become isolated, and live with the physical and psychological consequences of IPV. Research suggests that trauma informed nursing practice is needed to support teen mothers in violent intimate relationships to spin a new web.a

  • Rich, A. A Wild Patience Has Taken Me This Far, poems 1978-1981. WW. Norton and Company; 1981.


Transgender Patient Care


Our current featured article is by Rebecca M. Carabez, PhD, RN ;Michele J. Eliason, PhD and Marty Martinson, DrPH title “Nurses’ Knowledge About Transgender Patient Care: A Qualitative Study.” This article is available for download at no cost while it is featured on the ANS website!  Dr. Eliason sent this message about her personal experiences embarking on a career focused on LGBTQ health:

In 1988, I started my first study of LGBTQ issues in nursing, and I was NERVOUS! I had escaped a homophobic healthcare clinic setting for the supposedly academic freedom environment of the university the year before, but they had hired me as a developmental psych person. Nothing on my vita indicated an interest in LGBTQ issues at that

Mickey Eliason

Mickey Eliason

point, nor had these issues every been discussed in my formal education, except for an off-handed comment about homosexuality being a mental disorder in one psychiatric nursing course I took.

I talked to my research mentor at the time, who told me, “It’s all well and good that you do this type of research, but just make sure that you get 2 or 3 publications in legitimate areas for every one you do on this topic.” I did that, but even then, had some challenges when I came up for tenure.  I am glad to report that things have shifted in nursing since then, and articles on LGBTQ issues are becoming much more widespread. Now people are able to say LGBTQ and now what it means.  Even Donald Trump, halting and awkward as it was, uttered the initials at the Republican National Convention and called for equal rights (it might be the only sensible thing he has ever said on the campaign trail). We have made progress on LGB issues, but the growing edge of our movement in the past few years has been related to transgender issues.

In regards to this particular study, on nurses’ knowledge of transgender health care needs, our findings demonstrated that nurses’ willingness to work with diverse patients is laudable, but their lack of knowledge and fund of misinformation is quite alarming. This study was conducted in the San Francisco Bay Area, where presumably, nurses have much more exposure to LGBTQ issues than in many other places, but even here, we encountered negative attitudes and nurses saying that they never learned anything about this population in their educational programs or in continuing education.

This study was part of a much larger project on LGBTQ issues more broadly initiated by Rebecca Carabez, and a team

Rebecca Carabez

Rebecca Carabez

of nursing students worked on the project.  One identified as transgender, and we watched as they struggled with finding employment when the student’s appearance did not match their gender on legal documents, and who became more depressed as time wore on without meaningful employment. Transphobia has material consequences on individual’s daily lives—without adequate employment, transgender people are likely to live in poverty and suffer all the negative consequences of that poverty, from lack of any regular source of healthcare (leading to getting needed hormones and other treatments on the street), to “illegitimate” employment in the drug or sex trades, homelessness, and other serious issues.  We found in our study that many nurses laughed when talking about transgender issues—that nervous kind of laugh that means, “I’m really uncomfortable with this question.” They often gave long, rambling, circuitous answers to the questions that indicated that they really had no idea how to answer. Few were overtly negative about transgender patients, but imagine what it would be like for a transgender patient to try to communicate with a nurse who was that uncomfortable.

Marty Martinson

Marty Martinson

My co-authors and I had long discussions about gender.  We all identify as sexual minority women, but none of us as transgender or genderqueer. We tried to imagine ways to break down the gender binary that has been in operation in our own lives but like most others, we are somewhat entrenched in that system and it is hard to imagine life without the breaking down of people into two genders. It requires a radical transformation in thinking and in language itself. We firmly believe that this transformation is necessary, not just to improve services for transgender patients, but for all patient care, because the gender binary and gender stereotypes have hurt us all.

We hoped that our article might start some conversations among nurses about how to treat their transgender clients/patients more respectfully, but even more, about how to have hard conversations about the nature of gender and sexuality and ultimately, how we treat each other.  I am gratified that today, unlike the late 1980s when I started writing about LGBTQ issues in nursing, that there is now a willingness to publish articles on these topics and to discuss how to integrate them into  nursing education. Talking and writing about LGBTQ issues is a first step, but I challenge you to read the article and ask yourself, “What can I do personally to effect change for transgender patients in my nursing setting?”


Theory Integration to Explore Complexity


Our new featured article is titled “Using Theory Integration to Explore Complex Health Problems” by Brenna L. Quinn, PhD, RN, NCSN. We invite you to download the article while it is featured and return here to join discussion of these ideas.  In this message about her article, she describes the evolution of this article as a result of a rejection of another manuscript!

Brenna Quinn

Brenna Quinn

The idea for this article was actually born out of another article’s rejection. I met with my colleague Dr. Barbara Mawn to seek commiseration over the outright rejection and ask for help in writing an article about the importance of theory use and interdisciplinary integration, given that reviewer suggestions included removing the entire section on the study’s conceptual framework. Barbara’s mentorship was invaluable to the development of this article.  Said  conceptual framework is described in the ANS article as an example of interdisciplinary theory integration.

Use of theory to guide nursing research and clinical practice is underreported at best, but more likely is extremely underutilized. This is due to several factors, such as nurses receiving little education on theory use or confusion about how to interpret and apply theories to clinical practice.  Additionally, clinical nurses and nurse researchers may view nursing theories as too narrow to address the multi-faceted needs of patients or study populations.

Nurses know that they need to view patients and populations holistically, and cannot silo specific health problems.

Barbara Mawn

Barbara Mawn

For example: school nurses experience difficulty when assessing pain in children with intellectual and developmental disabilities. What kind of pain assessment tools has the nurse learned about? Has the school offered any continuing education opportunities regarding pain assessment for special populations? Do classroom teachers know which behaviors may be indicative of student pain? What is the ability of the student to report painful experiences?  Or, perhaps a nurse is working with a patient who has not been taking a medication prescribed for diabetes. The nurse must consider more than a presenting high blood glucose reading. Did the patient understand the nurse practitioner’s instructions for taking the medication? Can she access the pharmacy? Read the bottle? Administer the medication correctly? What is her level of cognition?

Many variables factor in to complex health problems faced by people today. However, this may not always appear clear to nurses and researchers when looking at nursing models. Using a non-nursing model, such as a model from psychology as described in the ANS article, can help frame the use of nursing theory components to the health problem at hand.

After reading this article, I hope nurses take the opportunity to explore both nursing and non-nursing theories that can guide and enlighten new approaches to clinical and research activities. Thank you for featuring this article on the ANS blog!

Quinn Picture1

Improving Mixed-methods Research in Nursing


The current featured article is titled “Mixed-Methods Research in the Discipline of Nursing” by Cheryl Tatano Beck, DNSc, CNM, FAAN and Lisa Harrison, MSN, PMHNP. We invite you to download this article while it is featured and return here to share your comments, questions and ideas for discussion.  Dr. Beck shared this background about her experiences with mixed methods:

This article was the culmination of a years’ worth of work that Lisa Harrison and I did. Lisa is a PhD student in

Cheryl Beck

Cheryl Beck

nursing at the University of Connecticut. She was assigned to me as a graduate assistant and for her assistance ship that year. Lisa worked with me on this review of mixed methods research in the discipline of nursing. Two years ago I presented one of my mixed methods studies in Boston at the Mixed Methods International Research Association’s inaugural research conference. At that conference there

were reports of the state of the science of mixed methods research in some disciplines but none focused on nursing. It was at that conference that I got the idea to conduct this focused review of mixed methods research in the discipline of nursing.

I began my interest in mixed methods research in earnest when about 6 years ago faculty at the University of Connecticut’s School of Nursing voted to add a mixed methods research design course to our core PhD curriculum. I was asked to teach this inaugural course and the rest is history. I have been teaching it every year since then. I have included in this blog a photo of my most recent mixed methods research class (spring 2016) when we

Lisa Harrison

Lisa Harrison

all went out for breakfast to celebrate the last day of class. Our PhD students are getting excited about the possibilities of mixed methods research. This past year we had 2 PhD students graduate who had conducted mixed methods dissertations.

I have conducted 4 mixed methods studies to date. Two have focused on secondary traumatic stress. One of these studies was with labor and delivery nurses and the other study was with certified nurse-midwives. Currently I have 2 other mixed methods studies in press. Both studies examined vicarious posttraumatic growth in obstetrical clinicians due to the struggles with caring for women during traumatic births.

We hope that our article published here in ANS will spark interest in students and faculty to conduct mixed methods research studies. This type of research can be the best of both worlds.

Front L toR: Lisa Sundean, Semin Park (PhD student in Business), and Wanli Xu. Back L to R: Cheryl Beck, Lucinda Canty, Lisa Nemchek, Nayomi Dawes.

Front L toR: Lisa Sundean, Semin Park (PhD student in Business), and Wanli Xu. Back L to R: Cheryl Beck, Lucinda Canty, Lisa Nemchek, Nayomi Dawes.

Workplace Mistreatment


The current ANS featured article is titled “Social Justice as a Lens for Understanding Workplace Mistreatment,” authored by Christine Moffa, MS and Joy Longo, PhD. In this article the authors explore the various forms of workplace mistreatment using Powers and Faden’s theory of social justice. Visit the ANS website now to download your copy at no charge while this article is featured!  Here is a message from Ms. Moffa about this

I have been interested in the issue of workplace mistreatment, particularly that faced by nurses, for a long time. My direct experience with this issue started during my first year as a nurse. I had never heard the unfortunately common

Christine Moffa

phrase “nurses eat their young” until I started working. Had I known, I might have studied something else! It sounds naïve now, but I was shocked that a profession built on caring was so cruel to its own members. My personal strategy for dealing with it was to keep moving until I found a work environment that didn’t expose me to being either a target or a witness to these negative behaviors. However, after continuing to hear from other nurses, new and experienced, how the problem persisted I knew more had to be done.

The idea for looking at workplace mistreatment as a social justice issue started with a conversation I had with one of my professors. Horizontal violence, incivility, and bullying have appeared in the nursing literature for over 30 years. It was time for a new viewpoint, one that could get people interested enough to want to do something about it, and at the same time acknowledge that patient outcomes were also a concern. Social justice was the answer.

Delving into the social justice literature I came across Powers and Faden’s (2006) theory. I believe viewing workplace mistreatment through their model of the six dimensions of well-being (health, personal security, respect, attachment, reasoning, and self-determination) highlights the gravity of workplace mistreatment, and demonstrates that this issue reaches far beyond the individual having a bad day at work, or having trouble getting along with other personalities. Powers and Faden’s (2006) theory is now the theoretical framework for my dissertation. The goal of this future study is to add to the knowledge base of workplace mistreatment so that the nursing profession, hospital administrators, and the public, will advocate for change and develop interventions to eradicate this problem.

This paper was a team effort, a culmination of my course work at the Christine E. Lynn College of Nursing at Florida Atlantic University. I would like to thank all of my professors past and present. In particular, I would like to thank my co-author Dr. Joy Longo who has devoted the last several years to studying horizontal violence and helped to bring this article up to the level worthy of appearing in ANS. Also thanks to Dr. Pat Liehr, who encouraged me to expand the section on social justice after my first draft.

Reference

Powers, M., & Faden, R. R. (2006). Social justice: The moral foundations of public health and health policy. New York: Oxford University Press.


Re-examining Marginalization


The first featured article for the latest issue of ANS is authored by Joanne M. Hall, PhD, RN, FAAN and Kelly Carlson, PhD, APRN-BC. The article addresses complex issues that perpetuate health disparities, and is titled “Marginalization: A Revisitation With Integration of Scholarship on Globalization, Intersectionality, Privilege, Microaggressions, and Implicit Biases.” The article is available to download at no cost while it is featured; I join the authors in inviting you to read it and return here to share your comments and ideas.  Here is a message from Dr. Hall about her work:

Why talk about marginalization? Marginalization refers to principles that can be transferred across contexts, yet we are learning that so many nursing problems, especially in the US, where healthcare is a pluralistic, patchwork

Joanne Hall

Joanne Hall

structure require attention to situation-specific factors, and situation-specific theories? The beginning of this thread of scholarship was the question, is there anything marginalized groups, or people in marginalizing situations have “in common?”  This not only included marginalization based on identity or group status, but on social processes, cultural expectations, environmental and socio-political factors. We agree with Chinn and Kramer that emancipatory knowledge is foundational to nursing science and practice.

There is an aspect of person that is potentially universal, a striving toward survival, thriving, and belongingness in such a way that supports diversity, equality, equity and justice. But this is not feasible for so many in the world at this time in history.

As a newly practicing RN, I was also, (in my spare time), an activist in the Catholic Worker Movement, and part of a group who opened a house of hospitality for women and children in Dubuque Iowa, my home town.  Eventually, we became a “discharge plan” and patients were sent from the local hospitals to “Catholic Worker House.”  The patients I cared for from noon to midnight in the psychic unit the night before might arrive in time for dinner the next evening and stay for two weeks.  This 6 years of my life was a great education about the highest-risk people in our communities.   We as a community combined providing food, clothing and shelter for those in immediate need with political action on larger justice issues.  At that time, liberation movements were growing in Latin America, and I became involved in discussions with various liberation and feminist theologians. In particular, I formed a partnership with my friend and mentor, now deceased, Manolo Barreno. Mano was a liberation theologian from Ecuador who had been thrown out by the Jesuits from a seminary in Rome for “associating with communists,” poor folks, who then not only took him in but supported his journey to the US,  to Iowa to finish his PhD at Aquinas Institute of Theology, which happened to be in Dubuque. Mano and I were fast friends, and became agitators in the group, pressing for justice not only in Latin America, and locally, but for structural changes in the Catholic Church itself. The movement by survivors of sexual abuse by ministers and priests (SNAP), was emergent.  Those who joined Mano and me pressed for women in the Catholic priesthood, and support for a local woman who taught at a Catholic school, and was fired specifically because she had a baby and was not married. We pressed for LGBT full recognition by the church.

My years in the Catholic Worker Movement eventually convinced me that this movement had a useful personalist philosophy, political analysis, an action orientation, especially focused on poverty, economic and anti-military issues, but that it would not take strong positions for women, African Americans, LGBTQ people, and in opposition to the emerging sexual abuse scandal, which eventually proved to be more expansive that anyone imagined at that time. (As I understand it, the movement has “come around” on these issues in recent years.)

I took a graduate course at Aquinas Institute in christology, the search for the historical Jesus. I realized the complex level of scholarship that had been done to determine hermeneutically, anthropologically, and historically who Jesus of Nazareth was.  I knew the power of writing that could influence sociopolitical and health outcomes.  I realized I was capable of taking a graduate class.

Fast forward, I decided that I might have more influence in solving the problems I became so familiar with as an activist, by contributing scholarship as a nurse leader as a nurse scientist. Working with Afaf Meleis and Patricia Stevens, we began in 1994 to answer that initial question, “Is there any thing, process, or set of elements, that is common in the experience of being marginalized?  Rather than an “identity categories” approach, the scholarship on marginalization focuses on the fact that anyone can be targeted, or suddenly find themselves in the high-risk situation of being marginalized.  This more contextual approach is consistent with an intersectionality framework, in which we realize that a person is potentially subject to marginalization based on a number of factors, and that, for a Black lesbian woman, for example, interpersonal slights may set off a whole energy-consuming and stressful problem-solving process for the woman, who is in a quandary about what the basis for the insult is.  “Is this based on race?  Is this because I am a woman and he is a man?  Do they know I am gay?  Is he just pissed off about something else? etc….  This is far less often a subjective experience of White, privileged males.  In fact research shows that those who are privileged, including White health care providers, have implicit biases, prejudices leading to racial microaggressions that White people are usually not aware they are perpetrating, and that has harmful effects on the target person.  We discuss much of this in this article, which is an update on recent scholarship relevant to marginalization.

Why should we as nurses be concerned with understanding political dynamics of the world we live in?  We hope this perspective helps nurses to be able to see the striving of human beings toward fullness of their lives, without amputating their culture, their understanding of their gender identity, their sexual orientation, their partner, their color, their religion, their abilities, and /or their substance use/abuse status. The emancipatory nature of human beings is as real as is their psychological, social, and physiological developmental processes. It is striving toward autonomy, self-determination, group-self-determination and respect as equals among other groups.  Therefore as nurses, we should assess where people are in terms of their own liberation.  This starts with safety, but goes far beyond, to wisdom, transcendence and action for those defined as “other.”  Or “them.”  This is advocacy.

I asked Dr. Kelly Carlson, coauthor what she might feel is relevant for this blog, and she replied that if we apply analysis to what is being said in the Trump presidential campaign about the Muslim parents who have spoken out in opposition we will see the discourses underlying such comments, and their implications. We are in an era in which, for instance, crowds, or mobs yelling “lock her up” about Hillary Clinton is reaching a level of social “acceptability.”  Instability and globalization have now led to xenophobia and the migrations of millions brown people from diverse regions affected by extreme poverty, political persecution and terrorist attacks. In the US, White privilege is systemic, and we have seen biased decisions by police resulting in statistics that look like systematic execution of people of color. The War on Drugs resulted in mass incarceration of African Americans and Latino/as.  The privatization of many of our prison facilities means that services, and even administration is “outsourced” to corporations, for profit, and the labor of prisoners becomes part of an enterprise reminiscent of slavery.

As psychiatric nurses, Kelly and I are particularly concerned with the “non-state” of mental health care following closure of state hospitals. The private corporations who stepped into that gap have been found to be far less concerned with quality of care, and are inadequate to meet the needs. Thus many enter the health system in costly ways, such as through the ED.  They fall through the cracks, at taxpayer expense.  Kelly pointed to another example of the return of a “slavery” system in the network of human trafficking, now pervasive in the US. We need to see the many ways people are marginalized, and how that affects health.  We need to end health disparities.

Nurses can develop knowledge through the lens of marginalization, viewing the person in part as an emancipatory being, striving toward impacting their sociopolitical environment.  It is about exerting self-will, and group self will.  We challenge nurse scientists, and health related scholars to include marginalization, and the real-life contexts of our patients, whether we are providing hands-on care, or making policy decisions at the population level. We can use social media, and mainstream media more effectively to shape the public discourse about health, and to define it broadly to include issues of discrimination, stigmatization, violence and symbolic violence.

Emancipatory knowledge will always need updating, as it is so closely tied to structures and processes of the larger social, cultural and political environment. It requires a historicist perspective.  We invite dialogue on this article, and the issues and questions it raises for nursing.